Alle indlæg af urtehave_com

KONDITION

STEP3

TRAINING LADDER FOR CHILDREN AND ADOLESCENTS:
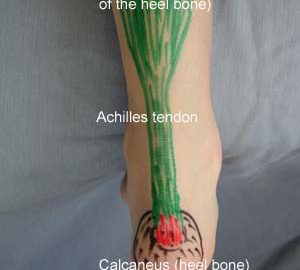
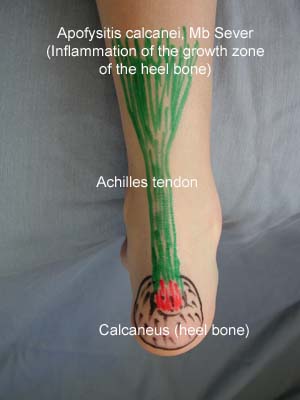
FOR INFLAMMATION OF THE GROWTH ZONE OF THE HEEL BONE
(APOPHYSITIS CALCANEI, MB SEVER)

STEP 3

The majority of young patients can manage with relief until the pain subsides, following which the sports activity can be slowly resumed. The following rehabilitation program will cover the needs for the vast majority of children with inflammation of the growth zone of the heel bone. Older teenagers involved in sports at a high level can advantageously use the rehabilitation program for adults.
KONDITION
Unlimited: Cycling. Swimming. Light jogging (few minutes) on a smooth surface.

UDSPÆNDING
(5 min)

Stand with the injured leg stretched backwards with the toes facing front. Slowly bend the knee so that the calf muscles become increasingly stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.

Stand with the injured leg outstretched with the ankle joint bent up against the wall. Press your abdomen against the wall so that the calf muscles become increasingly stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.


STYRKE
(10 min)


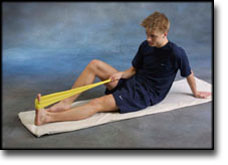
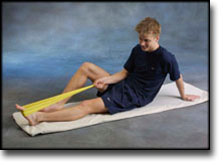
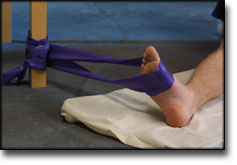
Sit on the floor. Tip the foot up and down with elastic under the forefoot so that the elastic becomes taut.

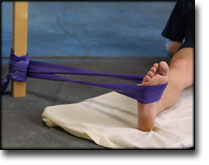
Sit on the floor. Tip the foot up and down with elastic on top of the forefoot so that the elastic becomes taut.

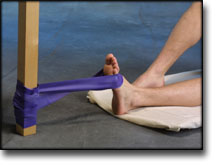
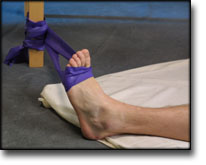
Sit on the floor. Tip the foot from side to side with elastic on the outer side of the foot, without moving the knee.

Sit on the floor. Tip the foot from side to side with elastic on the inner side of the foot, without moving the knee.

Stretching is carried out in the following way: stretch the muscle group for 3-5 seconds. Relax for 3-5 seconds. The muscle group should subsequently be stretched for 20 seconds. The muscle is allowed to be tender, but must not hurt. Relax for 20 seconds, after which the procedure can be repeated.

The time consumed for stretching, coordination and strength training can be altered depending on the training opportunities available and individual requirements.

KONDITION

STEP2

TRAINING LADDER FOR CHILDREN AND ADOLESCENTS:
FOR INFLAMMATION OF THE GROWTH ZONE OF THE HEEL BONE
(APOPHYSITIS CALCANEI, MB SEVER)

STEP 2

The majority of young patients can manage with relief until the pain subsides, following which the sports activity can be slowly resumed. The following rehabilitation program will cover the needs for the vast majority of children with inflammation of the growth zone of the heel bone. Older teenagers involved in sports at a high level can advantageously use the rehabilitation program for adults.
KONDITION
Unlimited: Cycling. Swimming.

UDSPÆNDING
(5 min)

Stand with the injured leg stretched backwards with the toes facing front. Slowly bend the knee so that the calf muscles become increasingly stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.

Stand with the injured leg outstretched with the ankle joint bent up against the wall. Press your abdomen against the wall so that the calf muscles become increasingly stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.

STYRKE
(5 min)

Sit on the floor. Tip the foot up and down with elastic on top of the forefoot so that the elastic becomes taut.

Sit on the floor. Tip the foot from side to side with elastic on the outer side of the foot, without moving the knee.

Sit on the floor. Tip the foot from side to side with elastic on the inner side of the foot, without moving the knee.

Stretching is carried out in the following way: stretch the muscle group for 3-5 seconds. Relax for 3-5 seconds. The muscle group should subsequently be stretched for 20 seconds. The muscle is allowed to be tender, but must not hurt. Relax for 20 seconds, after which the procedure can be repeated.

The time consumed for stretching, coordination and strength training can be altered depending on the training opportunities available and individual requirements.

KONDITION

STEP1

GENOPTRÆNING

TRAINING LADDER FOR CHILDREN AND ADOLESCENTS:
FOR INFLAMMATION OF THE GROWTH ZONE OF THE HEEL BONE
(APOPHYSITIS CALCANEI, MB SEVER)

STEP 1

The majority of young patients can manage with relief until the pain subsides, following which the sports activity can be slowly resumed. The following rehabilitation program will cover the needs for the vast majority of children with inflammation of the growth zone of the heel bone. Older teenagers involved in sports at a high level can advantageously use the rehabilitation program for adults.
KONDITION
Unlimited: Cycling. Swimming.

UDSPÆNDING
(5 min)

Stand with the injured leg stretched backwards with the toes facing front. Slowly bend the knee so that the calf muscles become increasingly stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.

Stand with the injured leg outstretched with the ankle joint bent up against the wall. Press your abdomen against the wall so that the calf muscles become increasingly stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.

Stretching is carried out in the following way: stretch the muscle group for 3-5 seconds. Relax for 3-5 seconds. The muscle group should subsequently be stretched for 20 seconds. The muscle is allowed to be tender, but must not hurt. Relax for 20 seconds, after which the procedure can be repeated.

The time consumed for stretching, coordination and strength training can be altered depending on the training opportunities available and individual requirements.

Treatment(2)

SportNetDoc

Local corticosteroid injection in sport: review of literature and guidelines for treatment.

Fredberg U. Scand J Med Sci Sports 1997 Jun;7(3):131-9.

The risks and benefits of local injection therapy of overuse sports injuries with corticosteroids are reviewed here. Injection of corticosteroid inside the tendon has a deleterious effect on the tendon tissue and should be unanimously condemned. No reliable proof exists of the deleterious effects of peritendinous injections. Too many conclusions in the literature are based on poor scientific evidence and it is just the reiteration of a dogma if all steroid injections are abandoned. The corticosteroids represent an adjuvant treatment in the overall management of sports injuries: basic treatment is ‘active’ rest and graduated rehabilitation within the limits of pain. With proper indications there are only few and trivial complications that may occur with corticosteroid injections. Guidelines for proper local injection therapy with corticosteroids are given.

Treatment(1)

Prevention and management of calcaneal apophysitis in children: an overuse syndrome.

Micheli LJ, Ireland ML. J Pediatr Orthop 1987 Jan-Feb;7(1):34-8.

Calcaneal apophysitis (Sever disease) is a common cause of heel pain, particularly in the athletically active child. Eighty-five children (137 heels) with calcaneal apophysitis were reviewed. Both heels were affected in 52 (61%) patients. The most common associated foot condition was pronation, occurring in 16 patients. Sixty-eight patients complained that pain was made worse by a specific sport, with soccer leading the list. All patients were treated with a physical therapy program of lower extremity stretching, especially of the heel cords, and ankle dorsiflexion strengthening. Soft Plastizote orthotics or heel cups were used in 98% of patients. Proper athletic shoewear was advised. All patients improved and were able to return to their sport of choice 2 months after the diagnosis. There were two recurrences.

Examination

SportNetDoc

Ultrasonography in the differential diagnosis of Achilles tendon injuries and related disorders. A comparison between pre-operative ultrasonography and surgical findings.

Paavola M, Paakkala T, Kannus P, Jarvinen M. Acta Radiol 1998 Nov;39(6):612-9.

PURPOSE.
To assess the value of US in the diagnosis of various Achilles tendon disorders.

MATERIAL AND METHODS.
Pre-operative US was compared with surgical findings in 79 patients with an Achilles tendon complaint.

RESULTS.
US was highly reliable for verifying a complete Achilles tendon rupture, only one false-negative US examination was found in the 26 surgically verified cases. For diagnosing retrocalcanear bursitis, US was accurate: 6 out of the 8 cases of bursitis were found and there were no false-positive cases. There were also no false-positive US findings in patients with peritendinitis/tendinitis, but 7 false-negative US cases among the 40 surgically verified peritendinitis/tendinitis patients indicated that a negative US finding in a clinically suspected case of peritendinitis/tendinitis is unreliable. US also seemed to be inadequate for differentiating partial tendon rupture from a focal tendon degeneration. Nevertheless, the occurrence and location of such a lesion could be adequately determined by US.

CONCLUSION.
US can reliably be used for locating the Achilles tendon abnormality, estimating its severity, and determining most of the conditions requiring surgical intervention. However, US is not completely reliable for diagnosing peritendinitis and tendinitis, and it cannot be used to differentiate partial tendon ruptures from focal degenerative lesions.

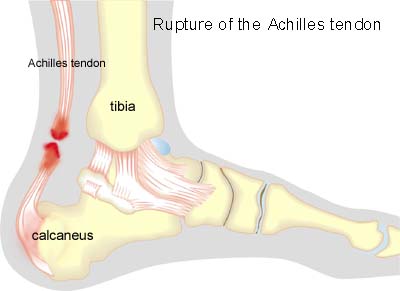
Rupture of the Achilles tendon

Diagnosis: RUPTURE OF THE ACHILLES TENDON
(Ruptura traumatica tendinis achilles)


Anatomy:
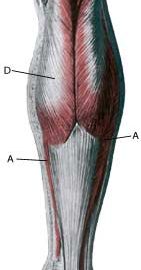
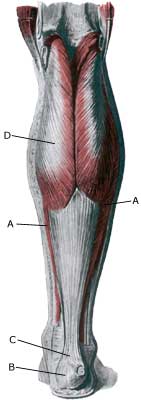
The calf muscle (M Gastrocnemicus) is comprised of two muscle heads which gather in a wide tendinous ligament and continue in to the Achilles tendon. Another of the larger calf muscles (M Soleus) is attached to the front side of the Achilles tendon and thus forms a part of the Achilles tendon. The Achilles is attached to the heel bone (calcaneus). The weakest area of the Achilles tendon is located approx. 3 cm. above the point of attachment to the heel bone.

  1. M. soleus
  2. Tuber calcanei
  3. Tendo calcaneus (Achillis)
  4. M. gastrocnemius

LOWER LEG FROM THE REAR

Cause: Full or partial rupture of the Achilles tendon most usually occurs when the Achilles is stretched simultaneously with the calf muscle contracting (eccentric contraction), which happens for example when a badminton player lands after a smash and at the same time starts out to reach the net quickly. Full or partial rupture of the Achilles always occurs with the background of degeneration in the tendon. Under half the cases have experienced symptoms prior to the rupture, however, as good as all the tendons show signs of degeneration during the subsequent examination.

Symptoms: Sudden pain in the Achilles tendon, where there is often a sensation of feeling and hearing a “crack”. Many believe that they have been kicked from behind. The pain is aggravated when activating the Achilles (walking), pressure on the tendon and when stretching the tendon. It is often possible to feel a defect in the tendon, and it is usually impossible to walk on the toes.

Acute treatment: Click here.

Examination: In all cases when there is a sense of a “crack”, or sudden shooting pains in the Achilles tendon, medical attention should be sought as soon as possible. Ultrasound scanning is used to advantage when making the diagnosis, as even full ruptures can easily be overlooked without the aid of ultrasound scanning. Ultrasound scanning enables an evaluation of the extent of the change in the tendon; full or partial rupture, inflammation of the tendon (tendinitis), development of cicatricial tissue (tendinosis), clacification, inflammation of the tissue surrounding the tendon (peritendinitis) and inflammation of the bursa (bursitis) (article), (Ultrasonic image).

Treatment: Ruptures can be treated with bandaging or surgical intervention. Operation is usually recommended for athletes and others with physical work. A period of 9-12 months must in all cases be expected to elapse before the sports activity can be resumed on the same level. Shoes with a slight heel elevation will relieve the pressure on the Achilles tendon. Treatment with ice for a period of at least 20 minutes after straining the tendon is recommended as long as the tendon remains sore (article-1), (article-2), (article-3).

Bandage: Taping to relieve problems with the Achilles tendon is of questionable significance, but can be attempted as the tape will not invoke further injury if applied in the correct manner (tape-instruction).

Complications: If there is not a steady improvement in the condition an ultrasound scan should be performed to exclude a renewed rupture of the Achilles tendon or:

It is unfortunately often the case that it is not possible to return to the same level of sports activity despite correctly administered treatment and training. 

Special: As there is a risk that the injury can be permanent, all cases should be reported to your insurance company. It is important that running shoes fit well (tight heel cap, slight heel elevation, shock absorbing soles).

KONDITION

STEP4

TRAINING LADDER FOR CHILDREN AND ADOLESCENTS:
FOR INFLAMMATION OF THE ACHILLES TENDON
(TENDINITIS ACHILES)

STEP 4

The majority of young patients can manage with relief until the pain subsides, following which the sports activity can be slowly resumed. The following rehabilitation program will cover the needs for the vast majority of children with tendinitis at the Achilles tendon. Older teenagers involved in sports at a high level can advantageously use the rehabilitation program for adults.
KONDITION
Unlimited: Cycling. Swimming. Running with increasing distance on a soft surface.

UDSPÆNDING
(15 min)

Stand with the injured leg stretched backwards with the toes facing front. Slowly bend the knee so that the calf muscles become increasingly stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.

Stand with the injured leg outstretched with the ankle joint bent up against the wall. Press your abdomen against the wall so that the calf muscles become increasingly stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.

KOORDINATION
(5 min)

Seesaw. Balance on two legs, possibly using a hand as support against the wall, balancing subsequently on one leg without support. Look straight ahead and keep knees bent.

STYRKE
(10 min)

Sit on the floor. Tip the foot up and down with elastic under the forefoot so that the elastic becomes taut.

Sit on the floor. Tip the foot up and down with elastic on top of the forefoot so that the elastic becomes taut.

Sit on the floor. Tip the foot from side to side with elastic on the outer side of the foot, without moving the knee.

Sit on the floor. Tip the foot from side to side with elastic on the inner side of the foot, without moving the knee.

Stand with both forefeet on a stool or doorstep with the heel out over the edge. Slowly rise up on to your toes with your weight on the healthy leg. Go slowly down on the injured leg as far as you can go. Use the healthy leg to rise up on to your toes again. The exercise should be performed with stretched, as well as bent knee. Wearing a rucksack and gradually increasing the ballast in the rucksack can increase the load.

Stretching is carried out in the following way: stretch the muscle group for 3-5 seconds. Relax for 3-5 seconds. The muscle group should subsequently be stretched for 20 seconds. The muscle is allowed to be tender, but must not hurt. Relax for 20 seconds, after which the procedure can be repeated.

The time consumed for stretching, coordination and strength training can be altered depending on the training opportunities available and individual requirements.