Alle indlæg af urtehave_com

Treatment(2)

SportNetDoc

Elbow injuries in childhood.

Weise K, Schwab E, Scheufele TM. Unfallchirurg 1997 Apr;100(4):255-69

Fractures and dislocations of the elbow are some of the most common injuries in childhood and adolescence. The majority occur in sport and play activities, e.g., a fall from gymnastics apparatus or a bike, or from popular sports items, such as skateboards or in-line skates. The injuries can be divided into pure dislocations of the joint and fractures of the distal humerus, proximal radius and ulna, or combinations of both. In addition, extra- and intraarticular fracture types are defined, with the latter as partial or complete joint lesions. Dislocations of the elbow joint or the radial head can occur as single injuries or in combination with a fracture. Supracondylar fractures and avulsion fractures of the medial epicondyle are the most frequent extraarticular lesions of the distal humerus. Fractures of the lateral condyle prevail is incomplete intraarticular lesions. In the forearm, radial head and neck fractures are predominant while typical and atypical Monteggia injuries have a special status. The complex joint construction and the age-dependent appearance of the epiphyseal ossification centers sometimes make a correct radiological diagnosis difficult. The trauma history and an exact, clinical examination help to verify the injury, as do comparative X-ray studies of the uninjured side when necessary (but not routinely). Unlike other anatomical areas, most elbow injuries-even in the growing skeleton-are treated operatively. Hereby, the growth plates have to be respected using minimal amounts of small implants. Additional immobilization in a cast for 2-4 weeks is necessary in most cases but does not lead to a functional deficit-in contrast to adults. The implants should be removed as early as possible. Despite all therapeutic efforts, a significant number of late sequelae, such as malunions and functional impairment, can be seen. The rate of long-term complications increases in cases of untreated displacement of fragments or joint instability. Corrective measures are performed only in selected cases and after the growth plates are closed. Our own treatment regime is demonstrated using exemplary clinical cases of the different injuries and the results of a long-term follow-up study on sports injuries of the elbow in children. Errors in diagnosis and therapy, as well as possible complications, are pointed out.

Treatment(1)

SportNetDoc

The management of forearm fractures in children: a plea for conservatism..

Jones K, Weiner DS. J Pediatr Orthop 1999 Nov-Dec;19(6):811-5

A retrospective review was undertaken to evaluate the efficacy of primary nonoperative treatment (closed reduction and long-arm casting) along with pins and plaster as a salvage technique for those reduction failures. A total of 730 closed fractures (1987-1993) was compiled, of which 300 required closed reductions and casting. Excluded from the study were teenagers whose growth plates were closed. Of the 300 fractures requiring closed reductions, 22 went on to require remanipulations, and 12 required the use of pins-and-plaster technique to obtain or maintain satisfactory reduction. Complications in the group treated in this manner included two superficial pin infections treated with antibiotics and two forearms with moderate loss of pronation/supination not requiring treatment. We believe that closed reduction of pediatric forearm fractures remains the accepted standard and the technique of pins and plaster should be considered a reliable alternative for the unstable injuries.

Examination

SportNetDoc

Elbow effusions in trauma in adults and children: is there an occult fracture?

Major NM, Crawford ST. AJR Am J Roentgenol 2002 Feb;178(2):413-8

OBJECTIVE: The purpose of this study was to evaluate whether a detectable abnormality was present on MR imaging without a visible fracture on conventional radiography in the setting of trauma. A recent retrospective study based on the presence or absence of periosteal reaction on follow-up radiographs concluded that fractures were not always present. The discrepancies in the literature over the usefulness of joint effusions as an indicator of fracture caused us to evaluate whether fractures were present more often than identified by conventional radiography. To do this, we used MR imaging. MATERIALS AND METHODS: Thirteen consecutive patients (age range, 4-80 years; seven children and six adults), whose post-trauma elbow radiographs showed an effusion but no fracture, underwent screening MR imaging. RESULTS: All patients showed bone marrow edema. Four of the seven children had fractures on screening MR imaging, and all adults had some identifiable fractures. CONCLUSION: Preliminary data using screening MR imaging suggests that an occult fracture usually is present in the setting of effusion without radiographically visualized fracture.

Complications

SportNetDoc

Hyperextension injury to the PIP joint or to the MP joint of the thumb–a clinical study.

Jespersen B, Nielsen NS, Bonnevie BE, Boeckstyns ME. Scand J Plast Reconstr Surg Hand Surg 1998 Sep;32(3):317-21.

We present a prospective study of the diagnosis and clinical course of 60 patients with 57 pure hyperextension injuries to the proximal interphalangeal (PIP) joint of the long fingers (fingers 2-5) and seven injuries to the metacarpophalangeal (MP) joint of the thumb. Thirty four of the injuries (57%) were related to ball sports, and the ulnar fingers of the non-dominant hand were usually affected. There were 24 avulsion fractures at the site of the insertion of the volar plate on to the middle phalanx. Twelve (20%) initially presented with hyperextension instability, and this was usually associated with an avulsion fracture. Thirty four of the patients (57%) had symptoms for less than one month, while 10 (17%) complained of symptoms six months after the injury. Severe complications such as daily pain and stiffness were encountered in three cases. The triad sign (pain on extreme flexion and extension) was of no use as a diagnostic or prognostic factor, nor did the radiographic stress-view help to identify acute instability of the joint.

tape-instruction

Tapening


Type: FINGER TAPE:

Objective: Stabilise finger joints.

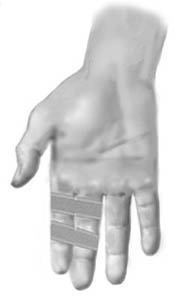
Application: Two anchor strips are applied, one on each side of the affected joint on the finger. Strips are similarly applied to the neighbouring finger. The two fingers are subsequently taped together with strips on the anchors. The healthy finger can in this manner stabilise the injured finger, whilst both fingers can still be bent and stretched.

Treatment(3)

SportNetDoc

Early active mobilisation of volar plate avulsion fractures.

Gaine WJ, Beardsmore J, Fahmy N. Injury 1998 Oct;29(8):589-91.

This is a prospective follow up of 190 consecutive cases of volar plate avulsion fractures. A standard management regimen of immediate, active movement was followed in all cases and physiotherapy was rarely required. Of the 190 patients, 162 were followed up for at least one year. An excellent or good outcome was achieved in 98 per cent. Patients presenting more than three weeks from injury had a worse outcome. The size and displacement of the avulsed fragment did not affect the outcome. For the stable joint, early active mobilisation with minimal or no splintage provides a good result.

Treatment(2)

SportNetDoc

Role of MR imaging in the management of “skier’s thumb” injuries.

Plancher KD, Ho CP, Cofield SS, Viola R, Hawkins RJ. Magn Reson Imaging Clin N Am 1999 Feb;7(1):73-84, viii.

“Skier’s thumb” is an acute rupture of the ulnar collateral ligament (UCL) of the metacarpophalangeal (MCP) joint of the thumb. As the method of choice in evaluating soft tissue injuries, MR imaging is useful in evaluating UCL injuries. This article reviews current concepts regarding the rupture of the UCL, including a study of 34 UCL injuries in which MR imaging was used as the main diagnostic tool. When correlated with surgical findings, MR imaging resulted in identifying UCL tears with 96% sensitivity and 95% specificity.

Treatment(1)

SportNetDoc

Sonography of the injured ulnar collateral ligament of the thumb.

Hergan K, Mittler C. J Bone Joint Surg Br 1995 Jan;77(1):77-83.

We used high-resolution ultrasonography to image the ulnar collateral ligament in 39 patients who had sustained recent injuries of the metacarpophalangeal joint of the thumb. All the patients were subsequently operated on and the lesions of the ligament were recorded. In 36 patients the preoperative ultrasonographic diagnosis was correct. Five of these showed no rupture of the ligament. In the other 31, ultrasonography correctly distinguished between rupture in situ (15) and rupture with dislocation of the ligament (16). Misdiagnosis by ultrasonography in three cases was due to delay of the investigation (three weeks after injury) in one, to technical error in one and to misinterpretation of the image in one.

Examination

SportNetDoc

The skier’s thumb.

Heim D. Acta Orthop Belg 1999 Dec;65(4):440-6.

The incidence of skier’s thumb (rupture of the ulnar collateral ligament of the first metacarpophalangeal joint) is increasing. To determine whether conservative or surgical treatment is indicated, ultrasound (US) and magnetic resonance imaging (MRI) have been advocated in the last few years. Surgery should be performed in the case of an unstable joint with a ligamentous tear or in the presence of a displaced bony fragment. Several techniques for surgical repair in acute and old ruptures are proposed. Conservative and postoperative treatment consists of immobilization of the joint in a splint or thumb spica cast for 4 weeks. The best results are obtained in bony avulsion fractures. Conservative treatment of lesions requiring surgical treatment may result in permanent disability of the joint; thus, correct diagnosis is mandatory.

KONDITION

STEP4

TRAINING LADDER FOR CHILDREN AND ADOLESCENTS:
FOR DISCLOCATION OF THE ELBOW
(LUXATIO ARTICULI CUBITI)

STEP 4

This rehabilitation program should only be considered in connection with an uncomplicated dislocation of the elbow, that has not required surgery. The rehabilitation to be followed must be agreed with your doctor if complications have arisen in the form of, for example, bone fracture, vascular damage or nerve damage.
KONDITION
Unlimited: Cycling. Running. Swimming.

UDSPÆNDING
(10 min)

Stand in a doorframe. Press your arms against the frame so that the front of your shoulders become increasingly stretched. Move your arms up and down the doorframe so that different parts of your muscles are stretched. Hold the position for 20 seconds and relax for 20 seconds before repeating.

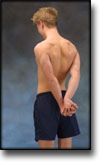
Stand with your hands together behind your back. Draw your shoulder blades together (imagine trying to hold a pencil between your shoulder blades). Hold the position for 10 seconds and rest for 10 seconds before repeating.

KOORDINATION
(5 min)

Seesaw. Balance on two legs, possibly using a hand as support against the wall, balancing subsequently on one leg without support. Look straight ahead and keep knees bent.

STYRKE
(45 min)

Stand and bounce a ball on the floor backwards and forwards from the injured to the good hand.

Support with both hands against a wall. Move slowly towards the wall and push away again. The exercise is performed like standing push-ups.

Hold an elastic band in the good arm. Take hold of the other end of the elastic with the injured arm and draw the injured arm downwards.

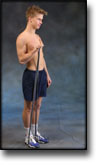
Put the elastic under your foot, and with the injured arm draw the other end upwards by bending your arm.

Stand with your side against a wall. Hold the elastic with the injured arm with elbow bent, upper arm 90 degrees away from your body and your hand at shoulder height. The palm of your hand should face the floor. Drawn your arm downwards and in front of your stomach.

Hold the elastic with the injured arm with elbow bent and your hand at shoulder level. Stretch your arm forwards so that the elastic is tightened.

Stretching is carried out in the following way: stretch the muscle group for 3-5 seconds. Relax for 3-5 seconds. The muscle group should subsequently be stretched for 20 seconds. The muscle is allowed to be tender, but must not hurt. Relax for 20 seconds, after which the procedure can be repeated.

The time consumed for stretching, coordination and strength training can be altered depending on the training opportunities available and individual requirements.